Prescribing Restraint: Understanding Why Withholding Antibiotics Is Sometimes the Most Protective Clinical Decision

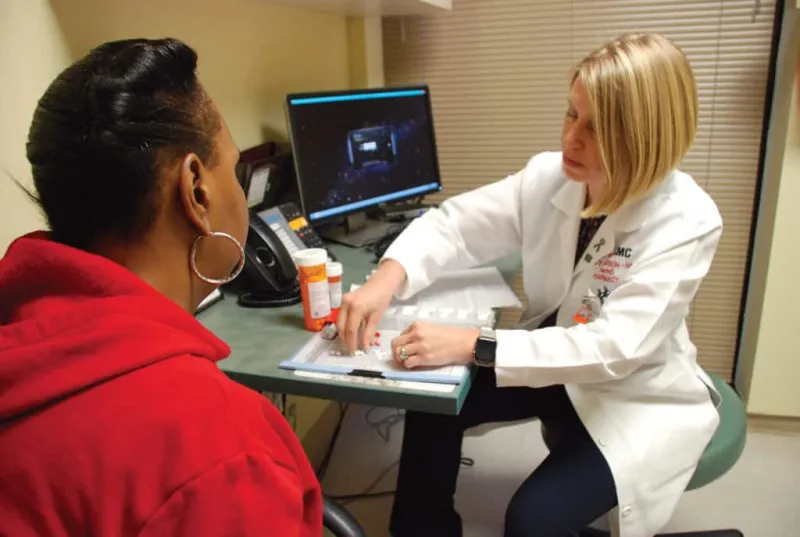
Photo: doctor discussing antibiotic prescription decision with patient in exam room, via img.freepik.com
There is a particular kind of reassurance that Americans have come to expect from a sick visit: a prescription. Not necessarily because the science demands it, but because the cultural script of medical care has long equated treatment with action and action with competence. Leaving a physician's office without a course of antibiotics for a respiratory illness can feel, to many patients, like leaving without help.
That expectation, however well-intentioned, is now one of the most significant drivers of a global health emergency. Antibiotic resistance—the process by which bacteria evolve to survive the drugs designed to kill them—is responsible for an estimated 35,000 deaths in the United States each year, according to the Centers for Disease Control and Prevention. The CDC further estimates that at least 28 percent of antibiotic prescriptions written in outpatient settings are unnecessary. The gap between what the science supports and what gets prescribed remains dangerously wide.
The purpose of this article is not to undermine confidence in antibiotics. It is to clarify when they are genuinely powerful, when they are clinically irrelevant, and when they may actively cause harm.
The Distinction That Changes Everything: Bacterial vs. Viral Infection
Antibiotics operate by disrupting bacterial cellular processes—interfering with cell wall synthesis, protein production, or DNA replication. They are precisely engineered tools for a specific biological target. Viruses, which lack the cellular machinery that antibiotics disrupt, are entirely unaffected by them.
This is not a subtle distinction. It is the foundational fact upon which every antibiotic prescribing decision should rest. And yet, a substantial proportion of antibiotic prescriptions in the United States are written for conditions that are overwhelmingly viral in origin: upper respiratory infections, acute bronchitis, most sore throats, the common cold, and the majority of sinus infections.
The clinical challenge is that viral and bacterial infections can present with overlapping symptoms. Both can cause fever, fatigue, congestion, and malaise. The differentiation requires clinical judgment, sometimes supported by diagnostic testing, and always informed by probability.
For context, consider acute pharyngitis—sore throat. Group A Streptococcus, the bacterial culprit that genuinely requires antibiotic treatment, accounts for only 5 to 15 percent of adult sore throat cases. The remaining 85 to 95 percent are viral. A rapid strep test, which takes minutes to administer, can reliably distinguish between the two. And yet strep tests are not universally performed before antibiotics are prescribed for sore throat. The result is a significant volume of antibiotic exposure that provides no clinical benefit while contributing to resistance and microbiome disruption.
The Microbiome: The Casualty Most Patients Don't Consider
The human gut harbors an estimated 38 trillion microbial cells—a community of bacteria, fungi, and other organisms that collectively perform functions critical to immunity, metabolism, and neurological health. This microbiome is not a passive bystander in antibiotic therapy. It is an active casualty of it.
Broad-spectrum antibiotics, by design, do not discriminate between pathogenic bacteria and beneficial commensal species. A standard five-to-ten-day course of amoxicillin or azithromycin can reduce microbial diversity in the gut by 25 to 50 percent, with some studies suggesting that full recovery of baseline diversity may take six months or longer—and that certain species may not recover at all.
The downstream consequences of microbiome disruption are not trivial. Reduced microbial diversity is associated with increased susceptibility to Clostridioides difficile infection—a potentially life-threatening gastrointestinal illness that kills approximately 15,000 Americans annually and is strongly linked to antibiotic exposure. It is also associated with heightened allergic response, impaired vaccine efficacy, and emerging evidence of metabolic and mood disruption through the gut-brain axis.
In other words, an antibiotic course that was never clinically necessary may leave a patient more immunologically vulnerable than they were before treatment. This is not a theoretical risk. It is a documented biological consequence.
Resistance: The Cumulative Cost Borne by Everyone
Antibiotic resistance is often framed as a future threat, a problem for the next generation of clinicians. The reality is that it is a present clinical constraint that is already limiting treatment options for serious infections.
Methicillin-resistant Staphylococcus aureus (MRSA), carbapenem-resistant Enterobacterales, and drug-resistant Neisseria gonorrhoeae are not hypothetical scenarios. They are organisms that American clinicians encounter in emergency departments, surgical wards, and outpatient settings with increasing frequency. Each unnecessary antibiotic course contributes to the selective pressure that drives resistance—not only in the individual patient, but in the broader microbial ecosystem they inhabit and share.
Patients sometimes reason that their single course of antibiotics is too small to matter at a population level. Epidemiologically, this reasoning does not hold. Resistance emerges through the aggregation of individual prescribing decisions. The patient who takes an unnecessary antibiotic for a viral sinus infection is not merely accepting personal risk; they are contributing a small but real increment to a collective burden.
A Framework for Informed Clinical Conversations
None of this means that patients should resist antibiotics when they are genuinely indicated. Bacterial pneumonia, urinary tract infections, Lyme disease, and streptococcal pharyngitis are among many conditions where timely antibiotic treatment is not just appropriate but potentially life-saving. The goal is not avoidance—it is precision.
For patients navigating this distinction, several practical principles apply:
Ask about the evidence, not just the prescription. When a provider recommends antibiotics, it is entirely appropriate to ask: Is this likely bacterial or viral? Has a diagnostic test confirmed or strongly suggested a bacterial cause? What is the evidence that treatment will shorten the course of this illness?
Understand watchful waiting as an active strategy. For many acute respiratory illnesses, the clinical standard of care is a period of observation—monitoring symptoms for signs of bacterial superinfection or clinical deterioration before initiating antibiotics. This is not passive medicine. It is a deliberate, evidence-based approach that avoids unnecessary treatment while maintaining readiness to act if the clinical picture changes.
Recognize the body's own capacity. The immune system is a remarkably sophisticated clinical instrument. For otherwise healthy adults, most viral upper respiratory infections resolve within seven to ten days. Supporting that resolution—through adequate hydration, rest, and symptomatic relief—is often the most effective intervention available.
Be aware of antibiotic stewardship programs. Most major US hospital systems and many outpatient practices now operate formal antibiotic stewardship programs designed to optimize prescribing decisions. These programs represent the clinical community's acknowledgment that restraint, applied rigorously, is a form of expertise.
The Harder Conversation Worth Having
Changing the cultural expectation around antibiotic prescribing requires candor from both clinicians and patients. Practitioners must be willing to explain, clearly and without condescension, why they are not prescribing—and patients must be willing to hear that explanation as evidence of clinical rigor rather than dismissal.
The most protective decision a provider can make is sometimes the one that involves writing nothing at all. At Power3 Medical, we believe that informed patients are better equipped to have these conversations—to understand that the prescription withheld, when the evidence supports withholding it, is not a failure of care. It is, in many cases, the most sophisticated clinical choice available.